What Is Srs Surgery Explained Clearly Today

Sex reassignment surgery or SRS has evolved from a niche medical procedure into a cornerstone of transgender healthcare globally. Once shrouded in secrecy and stigma, today’s gender-affirming surgeries reflect decades of medical advancements and societal progress. These procedures now provide individuals with the physical changes aligning with their gender identity, backed by rigorous medical standards and ethical guidelines.
From pioneering techniques in the 1950s to today’s refined surgical methods, SRS has transformed into a highly specialized field. Countries like Thailand and the United States lead in adoption rates, while legal frameworks in nations such as Argentina and Canada ensure accessibility. Yet, misconceptions persist—whether about irreversibility, eligibility, or post-operative outcomes—undermining the life-affirming impact of these surgeries. Understanding SRS requires navigating medical science, cultural perceptions, and ethical considerations.
Understanding Sex Reassignment Surgery: Historical Evolution and Modern Context

Sex Reassignment Surgery (SRS), now more commonly referred to as Gender Affirming Surgery (GAS), represents a pivotal milestone in transgender healthcare. This procedure encompasses a range of surgical interventions designed to align a person’s physical anatomy with their gender identity. The evolution of SRS reflects broader societal shifts toward inclusivity, medical advancements, and the recognition of gender diversity as a legitimate aspect of human experience. While terminology has evolved—shifting from "sex change" to "gender confirmation"—the core objective remains consistent: providing medically necessary interventions for transgender and gender-diverse individuals seeking bodily autonomy.
The historical trajectory of SRS is marked by significant milestones, from early experimental practices to today’s evidence-based, patient-centered approaches. Initially stigmatized and shrouded in controversy, SRS has gradually gained acceptance within medical, legal, and social frameworks, particularly as organizations like the World Professional Association for Transgender Health (WPATH) established clinical guidelines. Understanding this evolution is critical to contextualizing GAS within contemporary healthcare, where it is increasingly recognized as a standard of care rather than an elective cosmetic procedure.
Terminological Shifts: From SRS to Gender Affirming Surgery
The terminology surrounding gender-affirming procedures has undergone substantial transformation, reflecting broader cultural and medical progress. Sex Reassignment Surgery (SRS) emerged in the mid-20th century as the predominant term, emphasizing the medical alteration of sexual characteristics. However, this terminology carried inherent biases, reinforcing binary notions of sex and pathologizing transgender identities. In response, the medical community and advocacy organizations adopted Gender Affirming Surgery (GAS) as a more inclusive and accurate descriptor.
The shift to GAS underscores several key principles: - Patient-Centered Language: The term "gender affirming" prioritizes the individual’s self-identified gender rather than framing surgery as a correction of biological sex. - Holistic Healthcare Approach: GAS is part of a broader spectrum of gender-affirming care, which includes hormonal therapy, mental health support, and social transitioning. - Reduction of Stigma: By avoiding terms like "reassignment," which implies a deviation from a norm, GAS aligns with modern understandings of gender as a spectrum rather than a fixed binary.
Table of Contents
- Understanding Sex Reassignment Surgery: Historical Evolution and Modern Context
- Terminological Shifts: From SRS to Gender Affirming Surgery
- Historical Timeline of Gender Affirming Surgery
- Distinguishing Gender Affirming Surgery from Other Procedures
- Medical and Surgical Aspects of Sex Reassignment Surgery
- Feminizing Genital Surgery (FGS): Techniques and Procedural Breakdown
- Step-by-Step Description of Vaginoplasty: Pre-Operative, Intra-Operative, and Post-Operative Phases
- Comparison of Feminizing and Masculinizing Genital Surgery Techniques
Organizations such as the American Medical Association (AMA) and WPATH now advocate for the use of GAS, emphasizing that these procedures are medically necessary for many transgender individuals. This terminological evolution mirrors broader societal movements toward LGBTQ+ rights, where language plays a crucial role in shaping perceptions and policies.
Historical Timeline of Gender Affirming Surgery
The history of gender-affirming surgery is a narrative of medical experimentation, ethical debates, and gradual normalization. Below is a chronological overview of key milestones that shaped the development of GAS:
"The history of transgender healthcare is not just a story of medical progress but also a reflection of societal attitudes toward gender diversity. Early practices were often fraught with ethical dilemmas, but today’s standards are grounded in patient autonomy and evidence-based medicine." — Dr. Marci Bowers, Transgender Surgeon and WPATH Member
- Early 20th Century (Pre-1950s): Experimental Practices - The first documented sex reassignment procedure was performed in 1931 by Dr. Richard E. Lilian, a German surgeon, on Lili Elbe, a Danish transgender woman. This case, later popularized in the novel The Danish Girl, highlighted both the medical and ethical challenges of the time. - During World War II, Dr. Christian Hamburger in Denmark began administering estrogen to transgender women, laying the groundwork for hormonal therapy as a precursor to surgical interventions. - These early cases were rare, often performed in secrecy, and lacked standardized medical protocols.
- Mid-20th Century (1950s–1970s): Medicalization and Controversy - In 1952, Dr. Harry Benjamin, a German-American endocrinologist, published The Transsexual Phenomenon, providing a medical framework for understanding transgender identities. His work was foundational in legitimizing gender-affirming care. - The 1960s and 1970s saw the rise of phalloplasty and vaginectomy techniques, though these procedures were associated with high complication rates and limited accessibility. - The Stockholm Gender Identity Clinic, established in 1965 under Dr. Walter Pierron, became one of the first dedicated transgender healthcare centers, implementing psychological evaluations as a prerequisite for surgery.
- Late 20th Century (1980s–2000s): Standardization and Ethical Frameworks - The Harry Benjamin International Gender Dysphoria Association (HBIGDA), later renamed WPATH, published its first Standards of Care (SOC) in 1979, providing guidelines for transgender healthcare providers. These standards emphasized informed consent, psychological assessment, and real-life experience (RLE) as prerequisites for surgery. - Advances in microsurgery and tissue engineering in the 1990s improved outcomes for procedures like metoidioplasty and vaginoplasty, reducing complications and recovery times. - The 1990s–2000s also saw increased legal recognition of gender identity, with countries like Argentina (2012) and Malta (2015) becoming early adopters of self-ID laws, simplifying the process for transgender individuals to update legal gender markers without surgery.
- 21st Century (2010s–Present): Global Expansion and Inclusivity - The 7th WPATH Standards of Care (2011) introduced informed consent models, reducing the reliance on psychological evaluations and emphasizing patient autonomy. - Gender-affirming surgeries became more accessible in North America and Europe, with specialized clinics emerging in cities like San Francisco, Montreal, and Bangkok, the latter becoming a hub for affordable GAS due to lower healthcare costs. - 2020s: The COVID-19 pandemic highlighted disparities in access, with many transgender individuals facing delays in care. However, it also accelerated telemedicine integration for preoperative consultations and follow-ups. - Legal and social progress: Countries like Canada (2017) and New Zealand (2021) introduced gender marker X on official documents, reflecting broader recognition of non-binary identities. Meanwhile, U.S. states like California and New York expanded Medicaid coverage for gender-affirming surgeries.
Distinguishing Gender Affirming Surgery from Other Procedures
Gender Affirming Surgery is one component of a comprehensive approach to transgender healthcare, which may also include non-surgical interventions. Below is a comparative table outlining the key differences between GAS and other gender-affirming procedures:
| Procedure Name | Purpose | Common Terms Used | Medical Specialty Involved | |||||||||||||||||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Gender Affirming Surgery (GAS) | Permanently alters primary or secondary sexual characteristics to align with gender identity (e.g., vaginoplasty, phalloplasty, mastectomy, facial feminization). | Sex Reassignment Surgery (SRS), Gender Confirmation Surgery (GCS), Top Surgery, Bottom Surgery | Plastic and Reconstructive Surgery, Urology, Gynecology | |||||||||||||||||||||||||||||||||||||||||||||||
| Hormone Replacement Therapy (HRT) | Adjusts hormone levels to develop secondary sex characteristics (e.g., breast growth in trans women, facial hair reduction in trans men). | Cross-Hormone Therapy, Testosterone Therapy, Estrogen Therapy | Endocrinology | |||||||||||||||||||||||||||||||||||||||||||||||
| Facial Feminization/Masculinization (FFM) | Alters facial features to appear more feminine or masculine (e.g., jaw reduction, brow lift, tracheal shave). | Facial Gender Surgery, FFS, Forehead Contouring | Plastic and Reconstructive Surgery, Otolaryngology (ENT) | |||||||||||||||||||||||||||||||||||||||||||||||
| Voice Therapy | Modifies vocal pitch, tone, and resonance to align with gender identity. | Gender-Affirming Voice Training, Speech Therapy | Speech-Language Pathology | |||||||||||||||||||||||||||||||||||||||||||||||
| Electrolyte Therapy (for Adam’s Apple Reduction) | Reduces
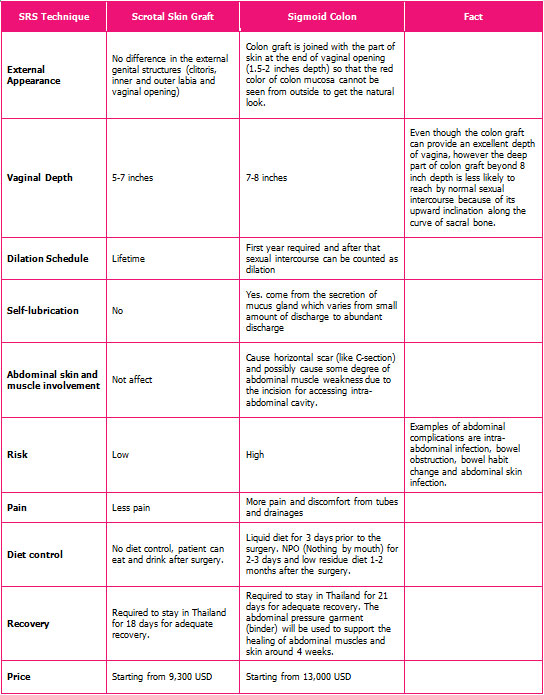
Medical and Surgical Aspects of Sex Reassignment SurgerySex reassignment surgery (SRS), also known as gender-affirming surgery (GAS), represents a critical intersection of medical science, surgical innovation, and personalized patient care. These procedures are designed to align a person’s physical anatomy with their gender identity, addressing both functional and psychological needs. The medical and surgical aspects of SRS encompass a wide range of techniques, each tailored to the unique goals of transgender and gender-diverse individuals. From feminizing genital surgery (FGS) to masculizing genital surgery (MGS), the field relies on specialized surgical expertise, advanced anatomical knowledge, and a multidisciplinary approach to ensure safety, efficacy, and patient satisfaction. This section explores the procedural intricacies, surgical specializations, technological advancements, and critical considerations for both patients and medical professionals.Feminizing Genital Surgery (FGS): Techniques and Procedural BreakdownFeminizing genital surgery (FGS) is one of the most common categories of SRS, aimed at constructing a vagina, vulva, and external genitalia that align with a female gender identity. The procedures typically include vaginoplasty, vulvoplasty, and orchiectomy, with vaginoplasty being the most complex and transformative. The choice of technique depends on factors such as anatomy, patient preference, and surgical expertise. The two primary methods for vaginoplasty are penile inversion and intestinal/skin graft techniques, each with distinct advantages and considerations. Penile inversion vaginoplasty is the gold standard for many surgeons due to its natural appearance and functional outcomes. This technique involves using the penile skin to create the vaginal canal while preserving sensation. The urethra is rerouted to its new position, and labia are constructed from scrotal skin. Alternatively, intestinal/skin graft vaginoplasty may be employed for individuals with limited penile skin or those requiring additional tissue for depth. This method often involves using a segment of the sigmoid colon or skin grafts, which can introduce higher risks of complications such as mucus discharge or bowel-related issues. Orchiectomy, the removal of testicles, is often performed concurrently with vaginoplasty. This procedure is typically straightforward, involving a small incision in the scrotum to extract the testes and spermatic cords. Orchiectomy eliminates endogenous testosterone production, further facilitating feminization when combined with hormone therapy.Step-by-Step Description of Vaginoplasty: Pre-Operative, Intra-Operative, and Post-Operative PhasesThe vaginoplasty procedure is meticulously planned to optimize outcomes while minimizing risks. Below is a detailed breakdown of each phase: Pre-Operative Preparations Patients undergoing vaginoplasty must complete a series of evaluations to ensure they are medically and psychologically prepared. This includes:Comparison of Feminizing and Masculinizing Genital Surgery TechniquesThe following table compares key surgical techniques in SRS, including success rates, recovery timelines, complications, and cost ranges. Data is based on studies from World Professional Association for Transgender Health (WPATH), American Society of Plastic Surgeons (ASPS), and peer-reviewed journals.
| |||||||||||||||||||||||||||||||||||||||||||||||||
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Velirium.